
Psychosis
What is Psychosis?
The word psychosis refers to an illness caused by a brain dysfunction that disrupts contact with reality. About 3% of the population, all causes taken together, will experience some form of psychotic episode, that is, a period during which they have psychotic symptoms. Although psychosis can affect anyone (regardless of social class, education level or ethnic group), it affects men slightly more than women, and it tends to start earlier in men. Peak onset is between the ages of 15 and 35.
Most people who have a psychotic episode will have a complete remission of their symptoms after this first episode. However, relapses are common: nearly 80% if treatment is stopped early. Like any other illness, psychosis can be treated. Taking antipsychotic medication regularly and as prescribed, a healthy lifestyle and good sleep hygiene, abstinence from drugs, moderate alcohol use, and medical and psychosocial follow-up all help reduce this risk of relapse.
LEARN MORE
Signs and symptoms
of Psychosis
In psychiatric jargon, we distinguish positive symptoms from negative symptoms. Negative symptoms are experienced by the patient as a lack of motivation, a lack of energy, and social withdrawal. The person may also become very inactive or lose interest in things they used to enjoy.
Positive symptoms are perceptions or ideas that are added on to external reality. They include, for example, visual or auditory hallucinations and delusions.

One of the cardinal symptoms of psychosis is delusional thinking. These bizarre or far-fetched ideas can appear during the prodrome (the period before the acute phase) or during the acute phase. When a person has these delusions, they believe they are right, but it is still possible to change their mind through discussion and argument.
As the symptoms intensify, the person becomes absolutely convinced of these ideas, and no argument can persuade them otherwise. This is then called psychosis. For example, the person may believe that people on the street are watching them or trying to hurt them, or that they have supernatural powers such as telepathy. Other people may believe that aliens or the government have put a chip in their brain to control them, that they have become the Messiah and have a mission to convert people, or that they are possessed by spirits or suffering from a serious illness, when this is not the case.
THOUGHT DISORGANIZATION
In addition to delusions and hallucinations, disorganized thinking is a central symptom of psychosis. It directly affects the ability to communicate with others, think clearly, and solve everyday problems.
In psychosis, the "thread" of thought is often disrupted. Speech can become difficult to follow, or even incoherent. There is usually a progression in the intensity of this symptom:
-
"Looped" or circular thinking (circumstantiality): At first, the person seems to go around in circles. They give an abundance of unnecessary details and struggle to get from point A to point B to express their idea.
-
Going off on tangents (tangentiality): As disorganization increases, the links between ideas weaken. The person changes the subject abruptly or only partly answers a question, because they forget their starting point or get carried away by a new thought.
-
Incoherent speech: In more severe forms, sentences follow one another without logic and the words themselves may seem unrelated. Speech becomes impossible for loved ones to understand.
- The impact on daily life: This difficulty organizing one's thoughts is hard on the patient. It creates a sense of isolation, because communication with loved ones becomes a source of confusion and frustration for everyone.
As with the other symptoms of psychosis, disorganized thinking is a sign of temporary brain dysfunction. It is not permanent: appropriate treatment and psychosocial follow-up can restore clearer thinking and help the person reconnect with others.
WHO CAN HAVE PSYCHOSIS?
Psychosis can affect anyone, in any country and in any social class. A full recovery is possible if the illness is detected and treated early enough.
The illness often starts a few years earlier in men (peak onset between ages 15 and 25) than in women (peak around ages 25 to 35).
According to the most recent studies, psychosis affects slightly more men than women and is slightly more common in urban areas than in rural settings. Those who use cannabis at a young age are at higher risk of developing psychosis, and ongoing drug use (especially psychostimulants and cannabis) is often responsible for a poorer outcome.
Causes of psychosis
Psychosis is a brain illness that leads to a loss of contact with reality. It produces an imbalance of brain neurotransmitters, particularly dopamine, which affects several cognitive domains.
There are many causes of psychosis. For example, in some people who have a biological vulnerability (due to several genes), added stressors can trigger the illness. These stressors are biological, such as drug use (cannabis, amphetamines, cocaine), and psychosocial (financial problems, family conflicts, social isolation). The illness usually appears in late adolescence or early adulthood, when personality and coping skills are still immature, which can make it harder to define a personal identity.
Late adolescence is generally a critical stage of development, when major social and psychological changes take place: individuation from the family (parental attachment gradually shifts toward relationships with peers), the development of interests, skills and hobbies, the discovery of intimacy and sexuality, the forming and maintaining of social relationships, career choice, and the start of employment or higher education. The young adult focuses their mental energy on consolidating their personality and defining their life plan. When psychosis sets in, it can interrupt this process.
There are different types of psychotic disorders including psychotic bipolar disorder (manic-depressive psychosis), schizophrenia, delusional disorder, substance-induced psychosis (commonly known as toxic psychosis) and others. It is the types of symptoms present, their proportion, and their duration and course over time that determine the exact nature of each psychosis. Another important factor to consider is the person's functioning during remission.
Although some psychotic disorders are not recurrent, most follow a course with episodic recurrences, which is why treatment is needed to prevent them. Rarely, sustained symptoms may require more specialized and intensive treatment.
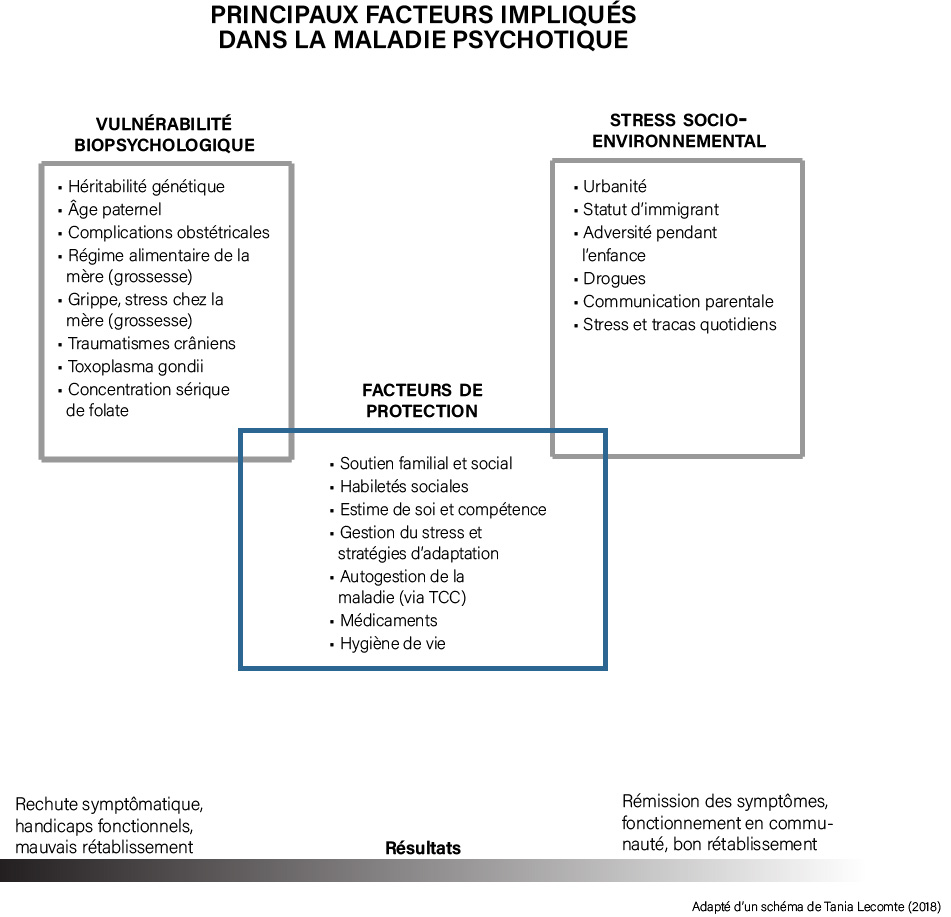
The diagram below summarizes the main factors involved in psychotic illness. The key point to take from this diagram is that it is the sum of all these positive and negative stressors, biological and social, that determines the final state of health. It is therefore important to pay attention to all of these factors to prevent relapses.

THE STAGES OF PSYCHOSIS
Although each psychosis presents and progresses differently, three phases, or “stages,” can be identified in most psychoses. The duration and intensity of the phases may vary.
1. PRODROME
During the prodrome, the person shows signs of psychosis, but they are milder. This period before full-blown psychosis is marked by changes in the person's thoughts, emotions, and perceptions. At this stage, those changes are still vague and hard to detect. They may simply take the form of greater distrust of loved ones, or of bizarre or abnormal responses. During this phase, functioning — that is, the ability to work or study — can be maintained, but more often it gradually declines. Symptoms are more often negative (isolation, withdrawal) and cognitive (problems with concentration and memory), and if there are positive symptoms (e.g. hallucinations, delusions), they are usually mild.
2. ACUTE PHASE
When the person is in the acute phase, the psychotic symptoms are clear: delusional thoughts, hallucinations and confused thinking. They cannot be persuaded that their thoughts are bizarre or abnormal; they firmly believe they are right. At this point, a psychiatric evaluation as soon as possible, along with antipsychotic medication, is essential for remission. In some cases, if the person's condition poses a danger, they may need to be hospitalized to stabilize them. Hospital stays are always kept as short as possible. Unlike the prodromal phase, a person in the acute phase has often become unable to work or study, because of the positive symptoms (auditory or visual hallucinations, hearing voices, delusional thoughts) and the disorganization that usually predominate. In the acute phase, affective symptoms may also appear, such as a low mood (frequent crying, suicidal thoughts or suicide plans, no longer wanting to eat or get out of bed) or an overly elevated mood (the person is overexcited, speaks very quickly, needs less sleep).
3. STABILIZATION
After a psychotic episode, the person is not immediately back on their feet and cannot necessarily return to work or school at 100% of their previous functioning. This is normal and part of recovering from the illness. This is called the (partial) remission phase: the period when the person still has some symptoms, at an intensity that varies from person to person, but is generally lower than during the acute episode.
During this period, the risk of relapse is highest, up to 80% without medication.
Most people will still have negative symptoms such as social withdrawal, isolation, lack of motivation and lack of energy, as well as cognitive difficulties, such as problems with concentration and memory (difficulty reading a book or watching a movie all the way through). In some people, disorganization and hallucinations or delusions may last longer (residual phase). Even so, at this stage it is quite possible to partially return to work or studies, one step at a time, adjusting medication when needed as part of closer follow-up during the first few months.
LEARN MORE
DRUG USE AND PSYCHOSIS
"A growing body of research shows that cannabis use, even in small amounts or occasionally, is a significant risk factor for psychosis."
CANNABIS, ALCOHOL AND OTHER DRUGS
The use of drugs and alcohol (in large amounts) reduces the effectiveness of treatment, increases vulnerability and can therefore lead to a relapse, that is, a return of the symptoms of psychosis. Recent studies, including those conducted at Clinique JAP, have shown that ongoing use is associated with a poorer course of symptoms and of social functioning.
Although cannabis use is widespread and often treated as ordinary, a growing body of research shows that cannabis use, even in small amounts or occasionally, is a significant risk factor for psychosis. The use of psychostimulants, such as cocaine and amphetamines (speed), as well as hallucinogens (e.g., ecstasy/MDMA), carries greater risks of psychosis and relapse than cannabis. Finally, these substances also increase the adverse effects of antipsychotics, either because their effects are additive (drowsiness) or because higher doses are needed to control the psychosis.
USING IS TAKING A RISK
It can be hard to convince young people to stop using after a first episode of psychosis or a relapse, because using is often part of their lifestyle and a way to socialize. Still, it is important to remember that just because someone uses and does not relapse once — or even several times — does not mean a relapse will never come. Drugs and alcohol are biological stressors for the brain, and it is the buildup of stressors that leads to psychosis. Because psychological or social stressors (job loss, a breakup, and so on) are not always under our control, using is taking a risk every time.
DID YOU KNOW?
It is well known that repeated relapses are harder to treat, that remission takes longer, and that they can sometimes lead to treatment-resistant psychosis, that is, psychosis that does not respond to the known antipsychotics and often requires one or more extra medications to control the acute phase.
In some cases, a stay in a detox or residential rehabilitation program for concurrent mental health and substance use problems may be necessary.
OUR MAIN PARTNERS
THE CONSEQUENCES OF PSYCHOSIS
When psychosis sets in, problems with concentration and organization pile up and make schoolwork increasingly hard. Many adolescents would rather leave school than fail academically or feel diminished in front of their peers. That takes them away from their main social setting, and without a place to practise, it is hard to learn social skills. In this context, forming intimate relationships becomes extremely difficult, because they are often distrustful. The illness also affects cognition and social skills. They may see isolation as a way to ease their distress. But as they lose their sense of identity and their bearings in the world around them, they lose a great deal of self-confidence.
When left untreated, psychosis causes a great deal of suffering, and its impact is felt to varying degrees in the person's social, family, school, and work life. The "psychosocial toxicity" of the illness can have serious consequences (homelessness, job loss, a shrinking social network, involvement with the justice system, poverty, increased substance abuse, suicide, and so on) that can throw a life into disarray. Early detection and intensive intervention can, however, lead to complete remission of symptoms and thus prevent prolonged suffering and disability.

